Field: Technology
Gene Editing: A Double-Edged Sword Promising Lifelong Health Yet Replete with Risks
Published | Technical Staff
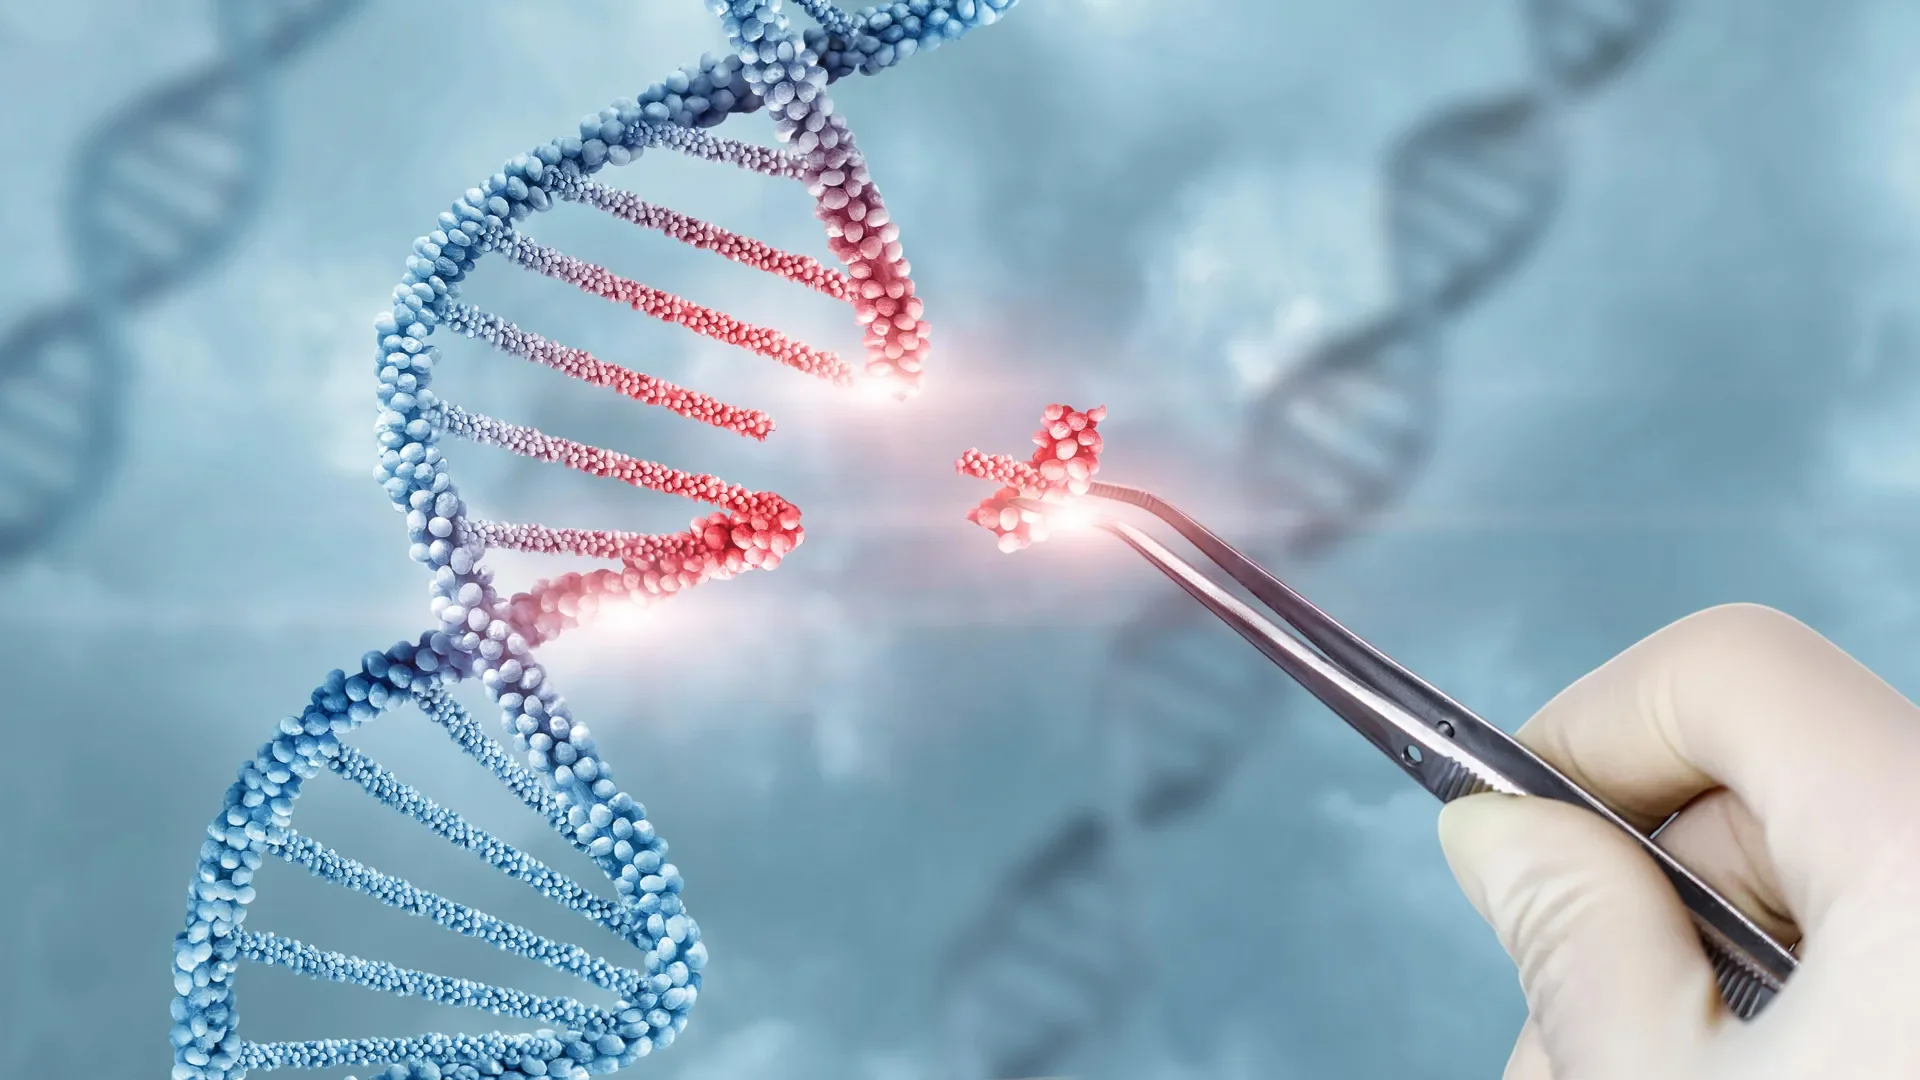
Visualization
Imagine a world where a single gene-editing intervention could obviate the perennial need for medication, forever altering the landscape of preventive healthcare. Recent advancements have illuminated the tantalizing prospect that such innovations might not only promise protection against maladies like heart disease and dyslipidemia but might also facilitate an era where genetic maladies could be more efficiently managed or even eradicated. While this groundbreaking approach offers the allure of lasting results from a singular treatment, the irreversible nature of permanent genetic modifications introduces a litany of ethical and safety dilemmas that demand rigorous scrutiny.
Current gene therapies have garnered attention for their ability to adjust genetic malfunctions associated with severe, often debilitating conditions. By manipulating genomic elements—either through the introduction of a healthy gene, silencing a deleterious one, or executing precise edits to DNA sequences—these therapies can achieve therapeutic outcomes that conventional medicinal approaches cannot match. Unlike pharmaceutical interventions that necessitate continuous administration, gene therapies are engineered to persist with a single dose—a characteristic aptly termed “one-and-done” treatment. Yet, this permanence harbors complexities; once a genetic modification ensues, it can become a lifelong reality, setting in motion changes that could take years or even decades to manifest with unintended consequences.
Central to this conversation is the modality by which genetic alterations are delivered into target somatic cells—usually via modified viral vectors. Although efficacious, these vectors can incite an immune response that may hinder or entirely preclude re-administration of the therapy, especially if adverse effects arise post-treatment. Hence, the very biology that allows for gene therapy’s unique efficacy also posits crucial questions regarding the flexibility and adaptability of healthcare responses to evolving patient needs.
Yet when the potential of gene editing spans common health issues like hyperlipidemia, cardiovascular disease, obesity, and diabetes, the stakes shift substantially. For individuals with rare genetic disorders, the imminent benefits of gene therapy may be unequivocal; these patients frequently face a dearth of effective treatments, rendering the prospect of a novel intervention particularly attractive. However, the ambiguity escalates when contemplating the application of gene editing for widespread diseases; established treatments are already in place, providing a measured avenue of ongoing intervention.
The complexities are further compounded by the need to satisfy rigorous safety standards, particularly when administering therapies within large populations. A rare but significant adverse event could translate to mass impact when millions are treated. In response to these multifaceted concerns, Eric D. Smith, M.D., and Venkatesh L. Murthy, M.D., Ph.D., cardiologists from University of Michigan’s Frankel Cardiovascular Center, propose a thoughtful evaluation framework that contextualizes the promise of genomic therapies against their inherent risks.
Their approach revolves around five salient factors: the severity of the disease being targeted and potential patient benefit; the landscape of existing treatment options that may provide a flexible and adjustable solution; durability of the targeted tissue to sustain long-term outcomes; delivery risks associated with the gene therapy itself; and the capability for robust long-term monitoring in large populations. Each of these dimensions initiates critical discourse surrounding the implications of adopting such revolutionary treatments into standard medical practice.
A primary concern revolves around the prospects of tracking adverse outcomes that might rear their heads only after years of treatment. Traditional clinical trials, typically structured around small cohorts and limited durations, often fall short of capturing exceedingly rare complications, underlining the necessity for a systemized approach that extends beyond initial research parameters. Such mechanisms, including patient registries, would provide invaluable insight into long-term efficacy and safety, thereby equipping the medical community to respond appropriately to the emerging complexities of genetic interventions.
As we stand at the precipice of this new frontier in medical science, it becomes increasingly evident that not every genetic alteration is suitable for permanent modification. Murthy emphasizes that while the technical capability to edit genomes may exist, the underlying pathophysiology of certain conditions may resist the application of fixed solutions. The nuanced balance inherent in adjusting medications for fluctuating health status underscores the prudence of restraint in permanently altering biological processes; without the capacity for continual adjustment, the threshold between beneficial treatment and adverse outcome may become perilously thin.
Ultimately, as gene editing continues to transition from experimental to mainstream applications, the promise of chronic disease mitigation or eradication must be considered within the broader context of potential risks. The medical community must navigate these waters with diligence, establishing a symbiotic relationship between innovation and ethical responsibility to ensure that the merits of gene therapy do not overshadow the imperative of patient safety and long-term well-being.
Current gene therapies have garnered attention for their ability to adjust genetic malfunctions associated with severe, often debilitating conditions. By manipulating genomic elements—either through the introduction of a healthy gene, silencing a deleterious one, or executing precise edits to DNA sequences—these therapies can achieve therapeutic outcomes that conventional medicinal approaches cannot match. Unlike pharmaceutical interventions that necessitate continuous administration, gene therapies are engineered to persist with a single dose—a characteristic aptly termed “one-and-done” treatment. Yet, this permanence harbors complexities; once a genetic modification ensues, it can become a lifelong reality, setting in motion changes that could take years or even decades to manifest with unintended consequences.
Central to this conversation is the modality by which genetic alterations are delivered into target somatic cells—usually via modified viral vectors. Although efficacious, these vectors can incite an immune response that may hinder or entirely preclude re-administration of the therapy, especially if adverse effects arise post-treatment. Hence, the very biology that allows for gene therapy’s unique efficacy also posits crucial questions regarding the flexibility and adaptability of healthcare responses to evolving patient needs.
Yet when the potential of gene editing spans common health issues like hyperlipidemia, cardiovascular disease, obesity, and diabetes, the stakes shift substantially. For individuals with rare genetic disorders, the imminent benefits of gene therapy may be unequivocal; these patients frequently face a dearth of effective treatments, rendering the prospect of a novel intervention particularly attractive. However, the ambiguity escalates when contemplating the application of gene editing for widespread diseases; established treatments are already in place, providing a measured avenue of ongoing intervention.
The complexities are further compounded by the need to satisfy rigorous safety standards, particularly when administering therapies within large populations. A rare but significant adverse event could translate to mass impact when millions are treated. In response to these multifaceted concerns, Eric D. Smith, M.D., and Venkatesh L. Murthy, M.D., Ph.D., cardiologists from University of Michigan’s Frankel Cardiovascular Center, propose a thoughtful evaluation framework that contextualizes the promise of genomic therapies against their inherent risks.
Their approach revolves around five salient factors: the severity of the disease being targeted and potential patient benefit; the landscape of existing treatment options that may provide a flexible and adjustable solution; durability of the targeted tissue to sustain long-term outcomes; delivery risks associated with the gene therapy itself; and the capability for robust long-term monitoring in large populations. Each of these dimensions initiates critical discourse surrounding the implications of adopting such revolutionary treatments into standard medical practice.
A primary concern revolves around the prospects of tracking adverse outcomes that might rear their heads only after years of treatment. Traditional clinical trials, typically structured around small cohorts and limited durations, often fall short of capturing exceedingly rare complications, underlining the necessity for a systemized approach that extends beyond initial research parameters. Such mechanisms, including patient registries, would provide invaluable insight into long-term efficacy and safety, thereby equipping the medical community to respond appropriately to the emerging complexities of genetic interventions.
As we stand at the precipice of this new frontier in medical science, it becomes increasingly evident that not every genetic alteration is suitable for permanent modification. Murthy emphasizes that while the technical capability to edit genomes may exist, the underlying pathophysiology of certain conditions may resist the application of fixed solutions. The nuanced balance inherent in adjusting medications for fluctuating health status underscores the prudence of restraint in permanently altering biological processes; without the capacity for continual adjustment, the threshold between beneficial treatment and adverse outcome may become perilously thin.
Ultimately, as gene editing continues to transition from experimental to mainstream applications, the promise of chronic disease mitigation or eradication must be considered within the broader context of potential risks. The medical community must navigate these waters with diligence, establishing a symbiotic relationship between innovation and ethical responsibility to ensure that the merits of gene therapy do not overshadow the imperative of patient safety and long-term well-being.